גושים במפשעה ובשק האשכים
נבדק על ידי ד"ר היילי וילאסי, FRCGP עודכן לאחרונה על ידי Dr Colin Tidy, MRCGPעודכן לאחרונה 7 בפברואר 2024
עומד בהנחיות העריכה של Patient
- הורדהורד
- שתף
- Language
- דיון
- Ask Patient
- גרסת שמע
- הוסף למקורות מועדפים בגוגל
אנשי מקצוע רפואיים
מאמרי עיון מקצועיים מיועדים לשימוש של אנשי מקצוע בתחום הבריאות. הם נכתבים על ידי רופאים מבריטניה ומבוססים על ראיות מחקריות, הנחיות בריטיות ואירופאיות. ייתכן שתמצא את גושים במפשעה מאמר מועיל יותר, או אחד מהאחרים שלנו מאמרי הבריאות.
Lumps in the groin and scrotum can occur at any age. Clinical assessment is needed to detect those which need urgent investigation or treatment. Usually a working diagnosis can be made clinically, and ultrasound is often helpful.
Causes of lumps in the groin and scrotum (aetiology)
Groin lumps
Painful lumps:
Tender בלוטות לימפה.
Strangulated femoral hernia.
Strangulated inguinal hernia.
Psoas abscess.
Painless lumps:
Skin swellings - eg, epidermal (sebaceous) cyst, דרמטיטיס ממגע.
Non-tender nodes.
Inguinal hernia.
Vascular:
Saphena varix (varicosity of saphenous vein at the junction with the femoral vein).
Scrotal lumps1
Painful lumps:
Torsion of a testicular or epididymal appendage.
Haematocele/haematoma.
Painless lumps:
Inguinal hernia (may sometimes be painful).
Spermatocele (feels similar to epididymal cyst but is filled with semen).
Skin swellings (as for groin lumps).
Less common causes of scrotal swelling include:
Idiopathic scrotal oedema (mainly children).
זיהומים:
Syphilitic gumma of the testis (round, hard, insensitive mass, indistinguishable from a tumour).
Tuberculous epididymitis.2
דלקת לבלב (fluid may track down the retroperitoneal compartment into the inguinal canal and scrotal sac).
Complications of peritoneal dialysis and ventriculoperitoneal shunts.
Crohn's disease manifestations: אריתמה נודוזום ו pyoderma gangrenosum.
Metastases (mainly from penile lesions).
Congenital abnormalities of lymphatic vessels (Milroy's disease).
Generalised oedema.
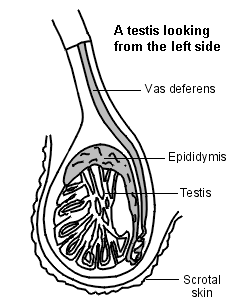
Anatomy of structures in the groin and scrotum
מבט חתך רוחב
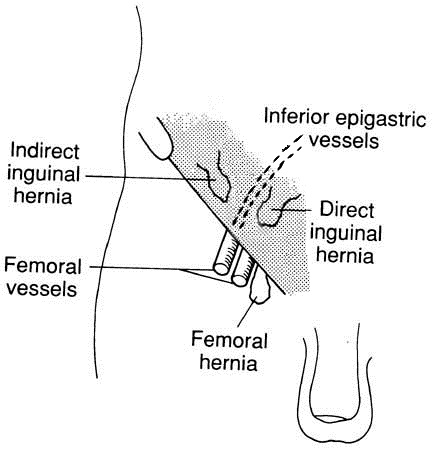
בקע מפשעתי
הערכה1
היסטוריה
כאב.
Duration and speed of onset (sudden in testicular torsion, more gradual in epididymo-orchitis).
Change in size.
Trauma.
Note whether it reduces (eg, on lying down).
Previous episodes. (Those with testicular torsion may have had previous self-limiting episodes.)
Associated symptoms:
Urethral discharge or dysuria (suggests epididymo-orchitis).
Abdominal pain, nausea and vomiting (can occur with testicular torsion).
Back pain, weight loss, dyspnoea (can occur with metastatic testicular cancer).
Parotid swelling (mumps orchitis).
בדיקה1 3
This should be carried out with the patient both standing and supine - hernias, varicoceles and saphena varix are more prominent when the patient is standing.
Check the normal structures and landmarks, which are:
Inguinal ligament.
Femoral artery.
Pubic tubercle.
Testis.
Epididymis.
Spermatic cord.
When examining the lump, note:
Tenderness: suggests infection or ischaemia, so think of testicular torsion, a strangulated hernia, epididymo-orchitis or psoas abscess.
Consistency of swelling: firm or solid for malignancy, soft and fluctuant for a cyst or hernia.
Location relative to landmarks. Femoral hernias are below and lateral to the pubic tubercle but, in practice, it is not always possible to distinguish inguinal and femoral hernias.
Note whether you can you 'get above' the swelling (ie feel the upper border of it). You cannot 'get above' a hernia.
Testis:
Note whether the lump is separate from the testis.
Testicular lie (may be transverse or high-riding in testicular torsion).
Cremasteric reflex. In the normal reflex, light stroking of the inner thigh causes contraction of the cremasteric muscle and therefore the testis on that side is pulled up. If absent, and there is acute scrotal pain or swelling, suspect testicular torsion.
A cough impulse suggests hernia or saphena varix.
Transillumination: cystic swellings such as hydroceles transilluminate well; solid tumours and most hernias don't. Inguinal hernias in infants may transilluminate.
Skin changes - a raised papule, plaque, or ulcer suggests scrotal cancer (rare).
Presence or absence of lymphadenopathy.
It is not necessary to distinguish between direct and indirect inguinal hernias.
Varicoceles typically feel like a 'bag of worms' and are more often left-sided.
Scrotal swellings - urgent problems not to miss1
תסביב אשך
Requires a low threshold of suspicion and immediate referral:
May be difficult to exclude on clinical grounds; may mimic epididymo-orchitis.
Common in teenagers; rare >30 years of age.
Sudden or gradual onset; may have had previous self-limiting pain episodes.
Painful; usually severe pain, which may radiate to the abdomen; may have vomiting.
Cremasteric reflex is almost always absent.
Testis is often elevated or lying transversely.
Neonates - testis is hard, non-tender, and usually haemorrhagic.
סרטן האשכים
Most common in men aged 20-40 years; can occur in older men (usually lymphoma).
Usually presents with testicular enlargement.
Often painless and non-tender; there may be a dragging sensation. Pain is present in 20-30%.
May have back or flank pain, dyspnoea, supraclavicular lymphadenopathy, abdominal mass (enlarged para-aortic lymph nodes), weight loss, gynaecomastia, epididymo-orchitis, or hydrocele.
On palpation, solid/firm swelling involving all or part of the testis.
Inguinal hernias in infants, or if strangulated/obstructed
May enlarge with Valsalva-type manoeuvres, and disappear on lying down (if reducible).
Positive cough impulse; bowel sounds on auscultation.
May be features of strangulation or obstruction (abdominal pain and/or intestinal obstruction symptoms).
Cannot get above the swelling.
Squamous cell carcinoma of the scrotum
Extremely rare; usually only in men aged >50 years.
Raised papule, plaque, or ulcer on the scrotal wall; often purulent.
Inguinal lymphadenopathy may be present (due to metastases or infection).
The National Institute for Health and Care Excellence (NICE) guidance on suspected cancer recognition and referral for testicular cancer states:4
Consider a suspected cancer pathway referral for testicular cancer in men if they have a non-painful enlargement or change in shape or texture of the testis.
Consider a direct access ultrasound scan for testicular cancer in men with unexplained or persistent testicular symptoms.
Diagnosing lumps in the groin and scrotum(investigations)
Clinically suspected testicular cancer: do not wait for investigations, but refer urgently to be seen within two weeks by a urologist. Alpha-fetoprotein (AFP) and beta human chorionic gonadotrophin (beta-hCG) are tumour markers for testicular cancer - can arrange a blood test while awaiting appointment.
Where diagnosis is unclear, request urgent ultrasound of the scrotum and/or groin (almost 100% sensitive for testicular tumours). This is useful, for example, where the body of the testis cannot be distinguished or where it is not clear whether the swelling is testicular or extratesticular, and for hydroceles in adults (to exclude testicular cancer).
Tests as appropriate for sexually transmitted infections where there is epididymo-orchitis.
Acute lymphadenopathy may need investigation for limb or genital/sexually transmitted infection.
Persistent unexplained lymphadenopathy needs biopsy.
Inguinal hernias in baby girls probably merit investigation for androgen insensitivity syndrome.5
Management of lumps in the groin and scrotum
This depends on the diagnosis, but note that:
Immediate referral is necessary for:
Suspected torsion of the testis.
Strangulated or obstructed hernia.
Urgent referral/investigation is needed for:
Femoral hernias:
These are more likely to strangulate than inguinal hernias; if suspected, they should be referred for surgery to be considered.
Hydroceles:
In infants, these usually resolve spontaneously.
Hydroceles occurring in adults may be secondary to testicular tumour or infection and should be investigated - request urgent ultrasound for hydrocele in men aged 20-40 years.1
Prevention of lumps in the groin and scrotum
Testicular cancer may present as a painless testicular swelling, and is often curable if treated early. Testicular self-examination may have a role in the early detection of testicular cancer. As for any lump, early consultation for testicular swellings should be encouraged.
עדכונים בלעדיים לאנשי מקצוע בתחום הבריאות
הישאר מעודכן עם העדכונים הקליניים האחרונים, תובנות מקצועיות והנחיות מבוססות ראיות. הניוזלטר של Patient Pro אוסף תוכן חיוני לאנשי מקצוע בתחום הבריאות - נשלח ישירות לתיבת הדואר הנכנס שלך.
על ידי הרשמה אתה מקבל את שלנו מדיניות הפרטיות שלנו. באפשרותך לבטל את המנוי בכל עת. לעולם לא נמכור את הנתונים שלך.
קריאה נוספת והפניות
- Tiemstra JD, Kapoor S; Evaluation of scrotal masses. Am Fam Physician. 2008 Nov 15;78(10):1165-70.
- Walker NA, Challacombe B; Managing epididymo-orchitis in general practice. Practitioner. 2013 Apr;257(1760):21-5, 2-3.
- Acute scrotal pain or swelling, Clinical practice guidelines; The Royal Childrens Hospital Melbourne, January 2013
- הנחיות לסרטן האשכים; האגודה האירופית לאורולוגיה (2025)
- United Kingdom BASHH national guideline for the management of epididymo-orchitis; British Association for Sexual Health and HIV (2019)
- Scrotal pain and swelling; NICE CKS; August 2024 (UK access only)
- Viswaroop BS, Kekre N, Gopalakrishnan G; Isolated tuberculous epididymitis: a review of forty cases. J Postgrad Med. 2005 Apr-Jun;51(2):109-11, discussion 111.
- Jenkins JT, O'Dwyer PJ; בקעים מפשעתיים. BMJ. 2008 פברואר 2;336(7638):269-72.
- חשד לסרטן: זיהוי והפניה; הנחיות NICE (2015 - עודכן לאחרונה באפריל 2026)
- Deeb A, Hughes IA; Inguinal hernia in female infants: a cue to check the sex chromosomes? BJU Int. 2005 Aug;96(3):401-3.
- Wang KS; Assessment and management of inguinal hernia in infants. Pediatrics. 2012 Oct;130(4):768-73. doi: 10.1542/peds.2012-2008. Epub 2012 Sep 24.
- Rosenberg J; Pediatric inguinal hernia repair-a critical appraisal. Hernia. 2008 Apr;12(2):113-5. Epub 2007 Nov 30.
אודות המחברצפה בפרופיל המלא
עודכן על ידי

Dr Colin Tidy, MRCGP
רופא כללי, מחבר רפואי
MBBS, MRCGP, MRCP (Paediatrics), DCH
ד"ר קולין טיידי הוא רופא ב-NHS, הממוקם באוקספורדשייר.
אודות המבקרצפה בפרופיל המלא

Dr Hayley Willacy, FRCGP
רופא כללי, מחבר רפואי
MBChB (1992), DRCOG, DFFP, MRCOG (Part 1) MRCGP (2007), DFSRH (2013), MSc - medical education (2020)
ד"ר היילי וילאסי הייתה רופאה כללית ב-NHS שעבדה בצפון מערב אנגליה, ופרשה מעבודתה הקלינית בשנת 2022 לאחר 30 שנות עבודה.
גישה פשוטה לטיפולים ושירותי בריאות אמינים באינטרנט.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.





עוד באונקולוגיה
- אלפא-פטופרוטאין
- מיימת
- ניקור מיימת
- סרטן שלפוחית השתן
- גידולי מוח בילדים
- אנטיגן סרטן 125
- אנטיגן קרצינואמבריוני
- סרטן צוואר הרחם
- לוקמיה מיאלואידית כרונית
- Craniopharyngiomas
- סרטן הקיבה
- מחלות אבק תעשייתי
- לוקמיה בילדים
- מזותליומה ממאירה
- לימפומה של רקמת לימפה הקשורה לרירית (MALT)
- נוירובלסטומות
- גידולים נוירואנדוקריניים בלבלב
- רישום תרופות בטיפול פליאטיבי
- נגעים תופסי מקום במוח
- גידולים בעמוד השדרה